GLP-1 vs GLP-1/GIP: Evidence and Practical Guidance for Clinicians

In randomized trials at maximal tolerated doses, the dual GIP/GLP-1 agonist tirzepatide produced greater mean weight loss than the GLP-1 agonist semaglutide, according to the NEJM head-to-head trial, though both drug classes share a gastrointestinal-predominant side effect profile. Choosing between them still depends on approved indications, comorbidities, and individual tolerability. This comparison walks through mechanism, trial data, safety, and prescribing considerations, including why independently verified peptide quality matters for researchers working with these compounds, a focus we bring to our work at Boren Health.
TL;DR:
- Tirzepatide demonstrates significantly greater weight loss than semaglutide at 72 weeks, with a 6.5 percentage point difference in mean weight change.
- The dual GIP/GLP-1 activity of tirzepatide produces distinct metabolic effects, notably greater impact on lipid metabolism and body weight, compared to GLP-1 alone.
- Both drugs share gastrointestinal side effects, primarily nausea, diarrhea, and vomiting, which are more manageable through careful dose titration.
- Approved indications differ: tirzepatide is also authorized for sleep apnea and has a shorter cardiovascular safety record than semaglutide, which boasts extensive cardiovascular data.
- Confirming peptide quality via independent testing is essential for research validity and safety, especially when comparing or sourcing compounds outside commercial channels.
Table of Contents
- Why dual GIP/GLP-1 agonism changes the metabolic picture
- What head-to-head trials actually show
- Matching the evidence to approved indications
- Safety screening and contraindications to check first
- Titration, counseling, and what to expect over time
- Why lab-verified peptide quality matters for research use
- Weighing efficacy against the patient in front of you
- Comparing peptide vendors before you buy or research
- FAQ
- Sources
Why dual GIP/GLP-1 agonism changes the metabolic picture
GLP-1 receptor agonists like semaglutide act on a single target, the GLP-1 receptor, slowing gastric emptying, reducing appetite centrally, and boosting glucose-dependent insulin secretion. Tirzepatide activates both the GIP and GLP-1 receptors, and according to a peer-reviewed mechanistic review, this dual activation appears to produce complementary effects rather than simple additive ones.
The review describes several distinctions worth understanding:
- GIP receptor activation contributes direct effects on adipose tissue, including changes in lipid metabolism that GLP-1 alone does not produce.
- Tirzepatide shows imbalanced agonism, with relatively stronger potency at the GIP receptor than at the GLP-1 receptor, a signaling pattern that may underlie its larger effect on body weight.
- Both molecules use albumin-binding protraction strategies that allow once-weekly dosing, but their receptor engagement profiles differ enough to produce distinct downstream effects on insulin secretion and glucagon suppression.
- Central appetite suppression appears to operate through overlapping but not identical pathways between the two drug classes.
Pro Tip: Because gastrointestinal side effects stem from shared mechanisms such as delayed gastric emptying and central nausea pathways, managing dose titration carefully is crucial for tolerability.
What head-to-head trials actually show
The clearest comparative evidence comes from a randomized trial reported in the New England Journal of Medicine, widely referenced as SURMOUNT-5, which compared tirzepatide directly against semaglutide in adults with obesity.
- At 72 weeks, tirzepatide participants showed significantly greater mean weight loss than semaglutide participants, with a difference consistent with reported clinical trial results, as detailed in the SURMOUNT-5 trial.
- A higher proportion of participants on tirzepatide reached at least 20% total weight loss, a finding confirmed in the ACC journal summary of SURMOUNT-5.
- Gastrointestinal adverse events were the most common side effects in both arms, occurring at broadly similar frequency.
The 6.5 percentage point gap in mean weight change between tirzepatide and semaglutide at 72 weeks, documented in the NEJM trial, represents one of the largest head-to-head differences reported between approved obesity therapies to date.
This trial used a maximum-tolerated-dose design rather than fixed equidose comparison, which tends to widen observed efficacy differences while still reflecting how these drugs are prescribed in practice. Separately, the SURPASS program established tirzepatide’s glycemic effects in type 2 diabetes, with HbA1c reductions that compared favorably against GLP-1 monotherapy in several of those trials. Study populations varied: some trials enrolled people with obesity alone, others enrolled people with type 2 diabetes, and that distinction affects how directly the results generalize to a given patient.
Matching the evidence to approved indications
Trial results only matter when they map onto what each drug is actually approved to treat. The two classes now cover overlapping but distinct indications.
- Tirzepatide, marketed as ZEPBOUND for obesity, carries additional approval for moderate to severe obstructive sleep apnea in adults with obesity, a 2026 label expansion confirmed in the FDA press announcement.
- Semaglutide formulations, sold as WEGOVY and OZEMPIC, hold long-standing approvals spanning obesity, type 2 diabetes, and cardiovascular risk reduction, as detailed in the semaglutide FDA label.
- Patients with obesity alone and patients with coexisting type 2 diabetes tend to show different magnitudes of weight loss on either drug, since glycemic status influences energy metabolism and appetite regulation independently of the drug itself.
Cardiovascular outcome trials for tirzepatide remain less mature than the long cardiovascular safety record behind semaglutide, a gap worth tracking as longer-term data accumulate. For patients where cardiovascular risk reduction is the primary goal rather than weight loss alone, the established evidence base behind GLP-1 monotherapy still carries weight in that decision, a point explored further in this explanation of cardiovascular benefits with GLP-1 therapy.
Safety screening and contraindications to check first
Both drug classes carry a boxed warning tied to thyroid C-cell tumors observed in rodent studies, and prescribing decisions should start with a careful history.
- Personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2 is an absolute contraindication for both agents, per the ZEPBOUND label and the semaglutide label.
- Gastrointestinal adverse events, mainly nausea, diarrhea, and vomiting, are the most frequently reported side effects for both classes, and a StatPearls review notes these concentrate during dose escalation and ease with time.
- Gallbladder disease and pancreatitis have been flagged as signals in post-marketing surveillance for this drug class, warranting symptom counseling before initiation.
- Immunogenicity data in the ZEPBOUND label note a measurable incidence of anti-drug antibodies, though clinical significance in most patients appears limited.
- Rapid weight loss itself raises aspiration risk during anesthesia, a consideration increasingly flagged in pre-operative assessments for patients on either drug.
Pro Tip: Before prescribing, confirm thyroid cancer family history, ask about prior gallbladder disease, and set expectations that nausea typically peaks during the first few dose increases rather than persisting at a stable level.
Titration, counseling, and what to expect over time
Slow dose escalation is the single most effective tool for managing tolerability, since gastrointestinal side effects correlate closely with how quickly the dose increases rather than with the final maintenance dose alone.

Typical practice involves starting at the lowest labeled dose and increasing at four-week intervals, pausing or extending an interval whenever GI symptoms are prominent. The StatPearls review notes that smaller, more frequent meals during escalation phases and reserving antiemetics for select cases both improve adherence. Patients should understand that meaningful weight loss builds gradually over months, not weeks, and that stopping therapy without a maintenance plan is strongly associated with weight regain.
When to pause therapy or refer:
- Severe or persistent vomiting that risks dehydration or prevents oral intake.
- Symptoms suggestive of pancreatitis, including severe abdominal pain radiating to the back.
- Signs of gallbladder disease such as right upper quadrant pain or jaundice.
- Pregnancy or active pregnancy planning, since both drug classes require discontinuation.
Pro Tip: Document a clear discontinuation and monitoring plan at initiation, since many patients regain weight once therapy stops without structured follow-up.
Why lab-verified peptide quality matters for research use
For researchers working with tirzepatide, semaglutide, or related compounds outside standard pharmacy channels, confirming identity and purity before use affects both safety and the validity of any findings. High-performance liquid chromatography and mass spectrometry reports typically show a purity percentage, confirm molecular identity, and flag contaminants that would otherwise go undetected.
- A certificate of analysis should specify the testing method, measured purity, and any detected impurities, not just a pass or fail summary.
- Blind sample testing, where the testing lab does not know which vendor supplied the sample, removes an obvious source of bias from published results.
- A small research comparison can produce misleading conclusions if the underlying peptide samples differ in purity between groups, which is why published, vendor-attributed lab data matters for reproducibility.
Weighing efficacy against the patient in front of you
The weight loss gap between these two drug classes is real, but clinical decisions rarely come down to trial averages alone. Some patients value the added efficacy of dual agonism enough to accept a steeper initial tolerability curve, while others prioritize the longer track record and broader cardiovascular evidence behind GLP-1 monotherapy. Neither preference is wrong, and the best prescribing decisions treat this as a shared one, built around monitoring plans and honest conversations about what chronic therapy actually requires.
— Ross
Comparing peptide vendors before you buy or research
Choosing between drug classes is only half the equation when researchers also need confidence in what they are actually receiving. We built a comparison platform around independent HPLC and mass spectrometry results rather than vendor claims, covering many vendors across compounds including tirzepatide and semaglutide.
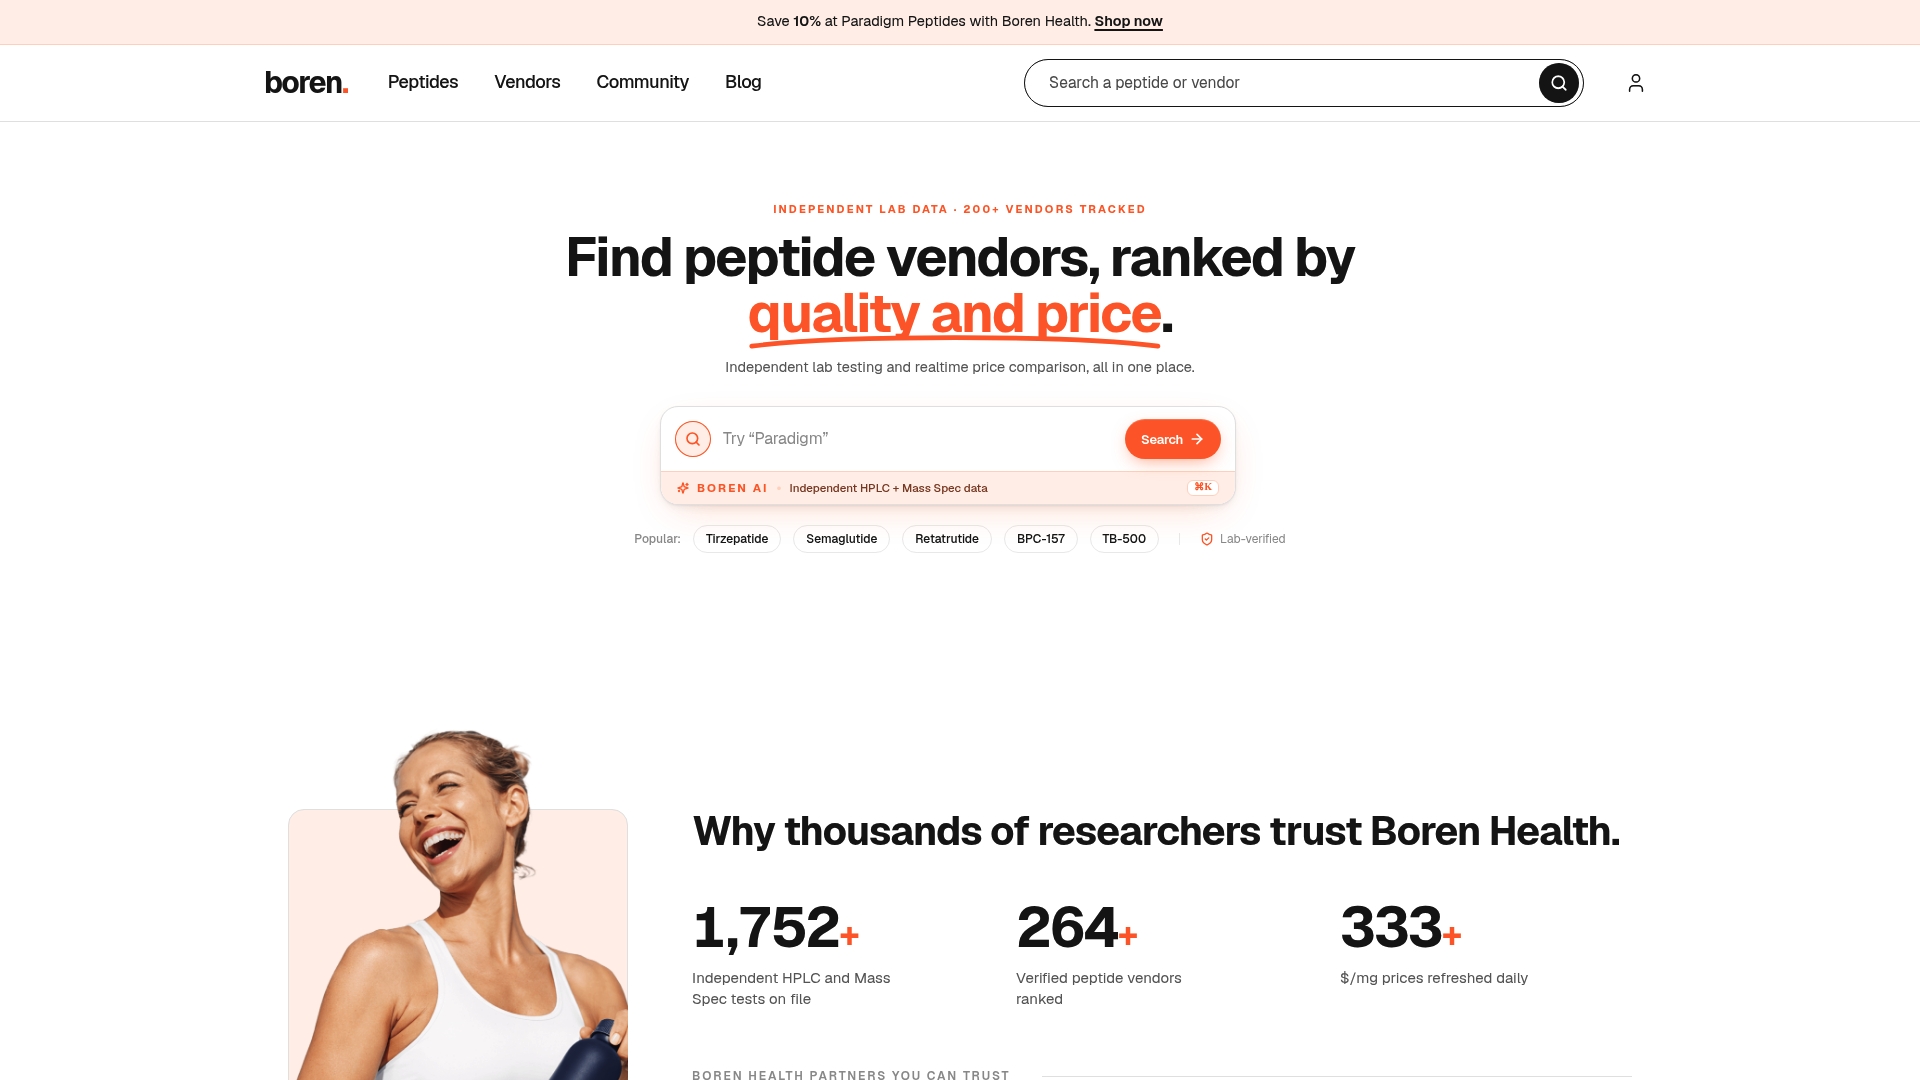
- Every lab result we publish, including failures, comes from blind sample purchases rather than vendor-submitted data.
- Price updates let researchers compare cost alongside verified purity rather than guessing at either one.
- We never sell peptides directly, which keeps our rankings free of pay-to-rank influence.
If verified vendor quality matters for your next research purchase, you can compare peptide vendors by research goal on our platform.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Is GLP-1 the same as GIP?
No, GLP-1 and GIP are distinct incretin hormones that act on separate receptors. Tirzepatide activates both receptors, while semaglutide and related drugs act only on the GLP-1 receptor, a distinction detailed in the mechanistic review on dual agonism.
Do you need a GIP with GLP-1?
A GIP component is not required for effective treatment, since GLP-1 monotherapy remains an approved and evidence-backed option for both obesity and type 2 diabetes. Adding GIP activity, as tirzepatide does, produced greater mean weight loss in the head-to-head NEJM trial, but the choice depends on individual goals and tolerability.
What does GIP mean in tirzepatide?
GIP stands for glucose-dependent insulinotropic polypeptide, a hormone receptor that tirzepatide activates alongside the GLP-1 receptor. This dual action is described in detail in the PMC review of GIP and GLP-1 mechanisms.
Is Ozempic GLP-1 or GIP?
OZEMPIC contains semaglutide, which acts only on the GLP-1 receptor and has no GIP receptor activity. Its approved indications and dosing are outlined in the semaglutide FDA label.
Sources
- Tirzepatide as Compared with Semaglutide for the Treatment of Obesity | NEJM
- Mechanisms of action and therapeutic applications of GLP-1 and dual GIP/GLP-1 receptor agonists - PMC
- SURMOUNT-5 summary and findings — American College of Cardiology Journal Scans (2025)
- StatPearls review on GLP-1 receptor agonists